SECTION 9.1
The digestive tract and accessory organs
Trace the path of food through the digestive tract and name the accessory organs that add secretions to it.
Learn
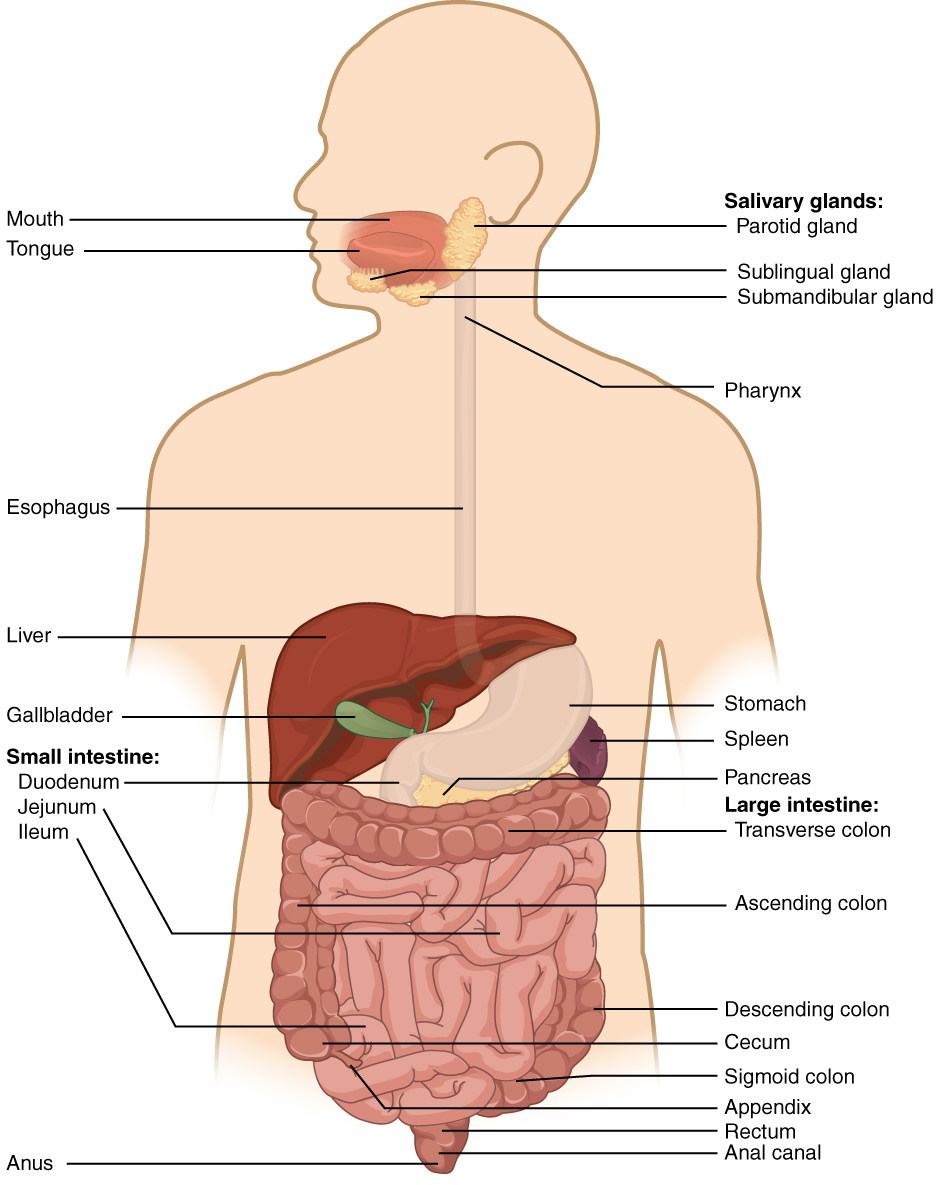
The digestive system has one long tube and several helper organs. The tube, called the digestive tract or alimentary canal, runs from the mouth to the anus and includes the mouth, pharynx, oesophagus, stomach, small intestine and large intestine. It is about nine metres long in an adult, and food travels through it in one direction while each region performs a particular task. The helper organs are the accessory organs: the salivary glands, liver, gallbladder and pancreas. They do not carry food, but they add secretions to the tract through ducts, and those secretions are essential for digesting food and absorbing nutrients. This section traces the path of food from mouth to anus and introduces the accessory organs that contribute to digestion.
Key Concepts & Topics
The digestive tract: mouth to stomach
Digestion begins in the mouth, where teeth cut and grind food and the tongue mixes it with saliva. The resulting soft mass is called a bolus. Swallowing moves the bolus into the pharynx and then into the oesophagus, a muscular tube about 25 centimetres long that carries it to the stomach. The oesophagus does not rely on gravity: its wall contains smooth muscle that produces waves of contraction called peristalsis, which push the bolus downward even when a person is lying down. The stomach is a J-shaped muscular sac that stores food, mixes it with acid and enzymes to form a semi-liquid paste called chyme, and releases it into the small intestine in controlled amounts. A ring of muscle at the lower end of the oesophagus, the lower oesophageal sphincter, normally prevents stomach contents from flowing back up.
For example: If the lower oesophageal sphincter is weak, acidic stomach contents flow back into the oesophagus and cause the burning sensation of heartburn.
 Enlarge illustration ↗
Trace the continuous route food takes from the mouth to the anus. Then find the liver, gallbladder and pancreas beside that route: they contribute secretions, but food does not pass through them.
Image source and licence
OpenStax College · Source image · CC BY 3.0. Original image, reproduced without alteration.
The small intestine and large intestine
The small intestine is where most digestion is completed and almost all nutrients are absorbed. It is about six metres long and has three parts: the duodenum, the jejunum and the ileum. The duodenum receives bile from the liver and gallbladder and digestive enzymes from the pancreas, as well as its own secretions. Its inner surface is folded into circular folds and covered with finger-like projections called villi, and the cells on the villi have further microscopic folds called microvilli. This folding increases the surface area enormously, which is what allows efficient absorption. The large intestine, about 1.5 metres long, receives the remaining material, absorbs water and electrolytes, and houses bacteria that ferment some fibre and produce vitamins. What remains is formed into faeces and stored in the rectum until it is eliminated through the anus.
For example: Removal of part of the ileum can impair absorption of vitamin B12 and bile salts, because that is where they are absorbed.
The accessory organs and their ducts
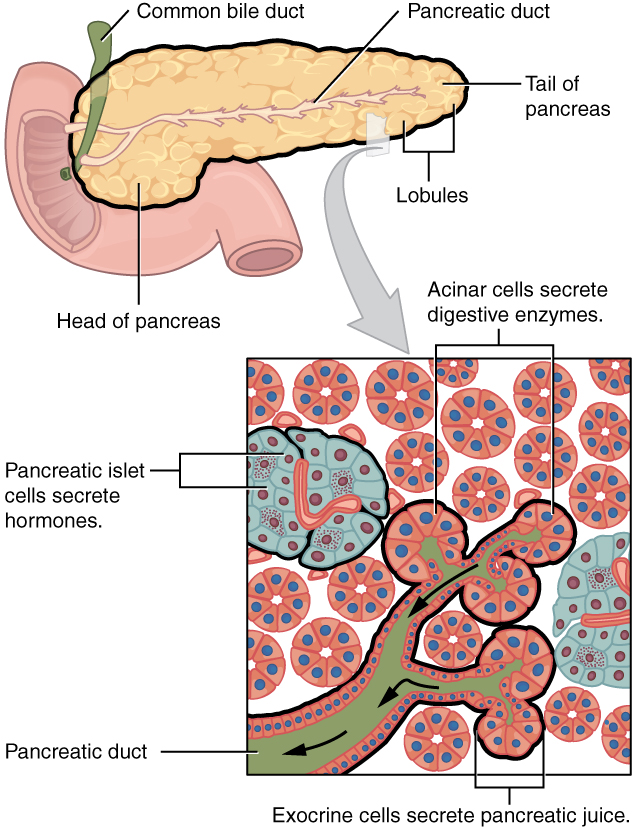
The accessory organs add secretions but do not carry food. The salivary glands produce saliva containing water, mucus, ions and the enzyme salivary amylase, which begins starch digestion; some also contain lysozyme, which acts on bacteria. The liver produces bile, a fluid that contains bile salts, which emulsify fats into small droplets so that enzymes can act on them. Bile is stored and concentrated in the gallbladder and released into the duodenum through the bile duct when fatty food arrives. The pancreas produces a broad set of digestive enzymes for carbohydrates, proteins and fats, plus a bicarbonate-rich fluid that neutralises stomach acid. These secretions reach the duodenum through ducts, which is why the liver, gallbladder and pancreas are described as accessory organs rather than parts of the tract itself.
For example: A gallstone blocking the bile duct prevents bile from reaching the duodenum, so fats are poorly digested and jaundice may appear.
 Enlarge illustration ↗
Compare the acini connected to ducts with the islets among them. Exocrine secretions travel through ducts to the intestine; endocrine hormones enter the blood. One organ contains two different routes of secretion.
Image source and licence
OpenStax College · Source image · CC BY 3.0. Original image, reproduced without alteration.
The wall of the digestive tract
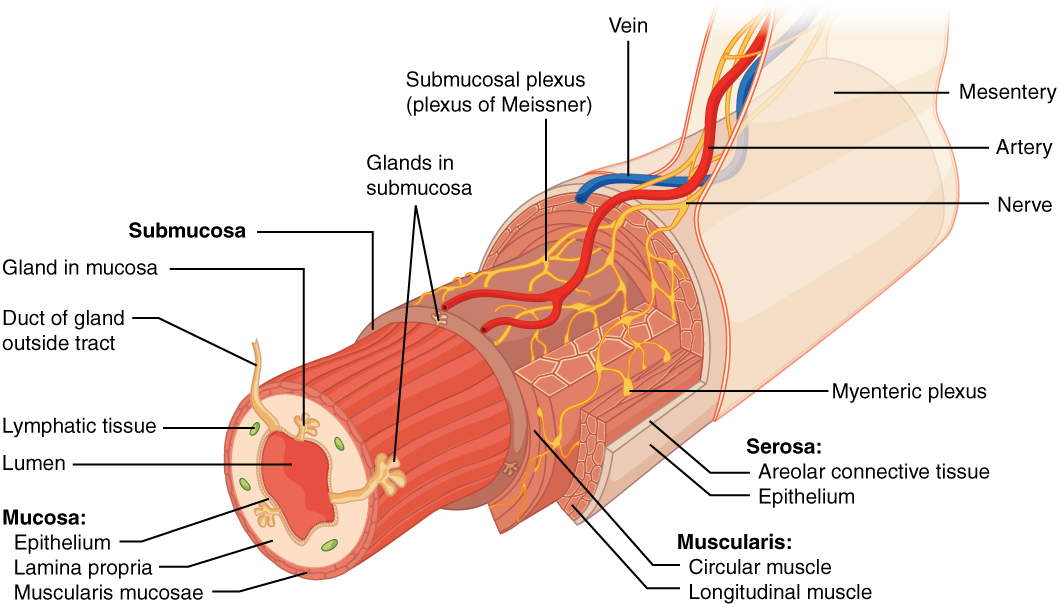
Most of the digestive tract is built from the same four layers, with variations suited to each region. The innermost layer is the mucosa, which lines the lumen and carries out secretion and absorption; its surface differs from region to region, from the protective stratified lining of the oesophagus to the absorptive villi of the small intestine. Around it lies the submucosa, containing blood vessels, lymphatics and nerves. Next is the muscularis, usually two layers of smooth muscle with fibres running in different directions; their coordinated contraction produces peristalsis, which moves contents forward, and segmentation, which mixes them. The outermost layer is the serosa, a smooth membrane that reduces friction with surrounding organs. A network of nerve cells embedded in the wall, the enteric nervous system, coordinates these movements locally and can act independently of the brain.
For example: The enteric nervous system can coordinate peristalsis even when the nerves connecting the gut to the brain are cut, which is why the gut is sometimes called a second brain.
 Enlarge illustration ↗
Start at the lumen, the space containing food, and work outward through the mucosa, submucosa and muscle layers. The lining contacts the contents; the deeper muscles move and mix them. This is a general plan, with differences between organs.
Image source and licence
OpenStax College · Source image · CC BY 3.0. Original image, reproduced without alteration.
Peritoneum and the layout of the organs
The abdominal digestive organs are arranged on a serous membrane called the peritoneum. The parietal peritoneum lines the abdominal wall, and the visceral peritoneum covers the organs. Between them is a thin film of fluid that allows organs to slide over one another as they move. The peritoneum also forms folds that hold organs in place and carry their blood vessels and nerves: the mesentery attaches the intestines to the posterior wall, and the omentum drapes over the abdominal organs and contains fat and immune tissue. Some organs, such as the kidneys, pancreas and parts of the duodenum, lie behind the peritoneum and are called retroperitoneal. Knowledge of this arrangement matters clinically because it determines how infection and fluid spread through the abdomen and where pain is felt.
For example: Because the pancreas is retroperitoneal, inflammation of the pancreas often causes pain that radiates straight through to the back.
Key facts to remember
- The digestive tract runs from mouth to anus and includes the mouth, pharynx, oesophagus, stomach, small intestine and large intestine.
- The accessory organs are the salivary glands, liver, gallbladder and pancreas; they add secretions through ducts but do not carry food.
- Peristalsis moves contents forward and segmentation mixes them; both are produced by the smooth muscle of the tract wall.
- The small intestine (duodenum, jejunum, ileum) is the main site of digestion and absorption, with villi and microvilli increasing surface area.
- The tract wall has four layers — mucosa, submucosa, muscularis and serosa — and the enteric nervous system coordinates its movements locally.
Example · Follow a mouthful of food. Teeth and tongue turn it into a bolus mixed with salivary amylase. Swallowing sends it into the oesophagus, where peristalsis pushes it to the stomach. There it is churned with acid and enzymes into chyme. It passes into the duodenum, where bile from the liver and gallbladder and enzymes from the pancreas are added. In the jejunum and ileum, digestion is completed and nutrients are absorbed across villi. The remaining material enters the large intestine, where water is absorbed and bacteria act, and the residue is stored in the rectum before elimination through the anus.
Read full notes
Read one topic at a time. These notes explain the mechanisms and relationships behind the key facts.
The digestive tract: mouth to stomach
The upper digestive tract prepares food for the small intestine. The mouth reduces the size of food particles, which increases the surface available to enzymes, and mixes them with saliva so that swallowing is possible. The oesophagus is a transit tube: it does not digest, secrete or absorb, and its only job is to deliver the bolus to the stomach reliably. The stomach then performs three tasks at once. It stores food so that eating can be intermittent while digestion is continuous. It churns and mixes food with acid and enzymes. And it releases its contents into the duodenum slowly, which gives the small intestine time to process them. Each region is therefore suited to a specific role rather than being a simple pipe.
The small intestine and large intestine
The small intestine is the centre of digestion and absorption, and its structure is built for surface area. Circular folds, villi and microvilli multiply the absorbing surface many times over, so a tube about six metres long behaves as if it had a far larger area. Each villus contains a capillary network and a lymphatic capillary called a lacteal, which is how absorbed nutrients reach the blood and fats reach the lymph. The large intestine works differently: it absorbs water and electrolytes rather than nutrients, hosts a large bacterial population, and compacts the residue into faeces. Its bacterial residents ferment fibre and synthesise some vitamins, including vitamin K and some B vitamins, which the body can then absorb. Together, the two intestines finish the job the upper tract began.
The accessory organs and their ducts
Accessory organs show how digestion depends on coordination. Saliva begins carbohydrate digestion in the mouth, which is useful because the food remains there only briefly. Bile does not contain digestive enzymes; it acts physically, breaking large fat droplets into smaller ones so that lipases can work on a much greater surface. Pancreatic juice supplies the enzymes for all three major nutrient classes, along with bicarbonate that protects the duodenum from stomach acid. Because each secretion arrives through a duct at a specific point, a blockage or loss of one organ has a predictable effect: without bile, fats are poorly digested and fat-soluble vitamins are poorly absorbed; without pancreatic enzymes, all three nutrient classes are poorly digested.
The wall of the digestive tract
The four-layer wall of the tract is a good example of a repeated design adapted locally. The mucosa changes dramatically from region to region: stratified in the oesophagus to resist abrasion, folded and glandular in the stomach to secrete acid and enzymes, and covered with villi in the small intestine to absorb. The muscularis is usually two layers with fibres at right angles, so contraction can narrow the tube and shorten it, producing the coordinated waves of peristalsis. The enteric nervous system within the wall contains as many neurons as the spinal cord and can run local reflexes on its own, which is why the gut continues to move after its extrinsic nerves are cut. The serosa allows the moving organs to slide without friction.
Peritoneum and the layout of the organs
The peritoneum is more than a wrapping. Because it forms folds, it suspends organs, carries their vessels and nerves, and provides a route for the spread of infection and fluid. The mesentery holds the intestines in place while allowing them to move, and the omentum contains fat and immune tissue and can wall off areas of inflammation. Knowing which organs are retroperitoneal is clinically important: inflammation there tends to cause pain that radiates to the back, and fluid or blood collects behind the peritoneal cavity. This is why the anatomy of the peritoneum is used daily in clinical reasoning about abdominal pain, ascites and the spread of disease.
Explore the diagram
Start with the whole view, then select a numbered structure. Compare the additional illustrations to connect what a structure looks like with what it does.
The digestive route
Trace the food pathway, then distinguish the accessory organs that add secretions.
More controls
01 / 7 Oesophagus
Oesophagus
A muscular tube carries swallowed material to the stomach.
Illustration credits
- Mariana Ruiz Villarreal (LadyofHats), Jmarchn · Digestive system without labels.svg · Public domain.

Adapted for this lesson: labels removed, artwork cropped or recoloured, and interactive teaching overlays added. Adapted artwork retains its source licence.
Organs of the abdomen
Anterior view of the digestive organs. Compare this with the posterior view to locate the kidneys and large vessels behind them.
More controls
01 / 6 Liver · mainly right
Liver · mainly right
The liver lies beneath the right dome of the diaphragm and extends across the midline.
Illustration credits
- Mariana Ruiz Villarreal (LadyofHats), Jmarchn · Digestive system without labels.svg · Public domain.
Adapted for this lesson: labels removed, artwork cropped or recoloured, and interactive teaching overlays added. Adapted artwork retains its source licence.
Connect the illustrations to the key ideas
UPPER TRACT · mouth → pharynx → oesophagus → stomach
The bolus becomes chyme; peristalsis moves contents even when lying down.
SMALL AND LARGE INTESTINE · duodenum, jejunum, ileum → large intestine
Villi and microvilli absorb nutrients; the large intestine absorbs water.
ACCESSORY ORGANS · salivary glands, liver, gallbladder, pancreas
They add saliva, bile and pancreatic juice through ducts.
Core Concepts Defined
- Digestive tract
- The continuous tube from mouth to anus through which food passes.
- Accessory organ
- An organ that adds secretions to the digestive tract but does not carry food.
- Bolus
- The soft mass of chewed food mixed with saliva.
- Peristalsis
- Waves of muscular contraction that push contents forward along the tract.
- Segmentation
- Local muscular contractions that mix contents rather than propelling them.
- Chyme
- The semi-liquid mixture of food, acid and enzymes produced in the stomach.
- Lower oesophageal sphincter
- The muscle ring that prevents stomach contents from refluxing into the oesophagus.
- Duodenum
- The first part of the small intestine, which receives bile and pancreatic enzymes.
- Jejunum
- The middle part of the small intestine, a major site of absorption.
- Ileum
- The final part of the small intestine, absorbing bile salts and vitamin B12.
- Villus
- A finger-like projection of the small intestine lining that increases surface area.
- Microvillus
- A microscopic fold on the surface of an intestinal cell, further increasing surface area.
- Large intestine
- The section that absorbs water and electrolytes and forms faeces.
- Salivary amylase
- An enzyme in saliva that begins the digestion of starch.
- Bile
- A liver secretion containing bile salts that emulsify fats.
- Gallbladder
- The sac that stores and concentrates bile and releases it into the duodenum.
- Pancreas
- An organ that supplies digestive enzymes and bicarbonate to the duodenum, and hormones to the blood.
- Mucosa
- The inner layer of the tract wall, responsible for secretion and absorption.
- Muscularis
- The muscle layers of the tract wall that produce peristalsis and segmentation.
- Serosa
- The smooth outer membrane of the tract that reduces friction.
- Enteric nervous system
- The network of neurons in the tract wall that coordinates local movement and secretion.
- Peritoneum
- The serous membrane lining the abdominal cavity and covering its organs.
- Mesentery
- The peritoneal fold attaching the intestines to the posterior abdominal wall and carrying vessels.
- Retroperitoneal
- Lying behind the peritoneum, as the kidneys and pancreas do.
Go deeper · worked example
Tracing food from mouth to anus
- Mouth and pharynx. Teeth and tongue reduce food to a bolus mixed with saliva, whose amylase starts starch digestion; swallowing moves the bolus into the pharynx.
- Oesophagus and stomach. Peristalsis carries the bolus down the oesophagus to the stomach, where acid and enzymes churn it into chyme; the lower oesophageal sphincter normally keeps it from returning.
- Duodenum. Chyme enters the duodenum, where bile from the liver and gallbladder emulsifies fats and pancreatic enzymes plus bicarbonate are added to digest nutrients and neutralise acid.
- Jejunum and ileum. Most digestion is completed and nutrients are absorbed across villi and microvilli; the ileum also absorbs bile salts and vitamin B12.
- Large intestine to anus. The remaining material enters the large intestine, where water and electrolytes are absorbed and bacteria act; faeces are stored in the rectum and eliminated through the anus.
Explain it yourself · Explain why the liver, gallbladder and pancreas are called accessory organs rather than parts of the digestive tract.
Reveal a model explanation
The digestive tract is the continuous tube that food actually travels through, from the mouth to the anus. The liver, gallbladder and pancreas are not on that route: food never enters them. Instead, they produce secretions that reach the tract through ducts. The liver makes bile, the gallbladder stores and concentrates it, and the pancreas supplies digestive enzymes and bicarbonate. These secretions are essential, because bile emulsifies fats and pancreatic enzymes complete the digestion of carbohydrates, proteins and fats in the duodenum. Because they contribute to digestion without carrying food, they are classified as accessory organs. The same logic applies to the salivary glands, which add saliva to the mouth.
Check
Answer three questions from this section — one easy, one medium and one hard. If you miss one, you get a fresh set with explanations for the last attempt.
Practise this sectionOpen all questions and filter by difficulty or Bloom levelReferences and review status
OpenStax, Anatomy and Physiology 2e, 23.1 Overview of the Digestive System and 23.2 Digestive System Processes and Regulation; Tortora & Derrickson, Principles of Anatomy and Physiology, 12e, ch. 24. Author review only; medical and French-language expert review pending.
Original teaching schematics. English and French wording is author-reviewed for study; anatomy and French-language expert review is pending. Checks are practice only, not a graded examination.
Practice progress is saved on this device for the current learner.